


 TR
 EN
 RU
 AR
 FR


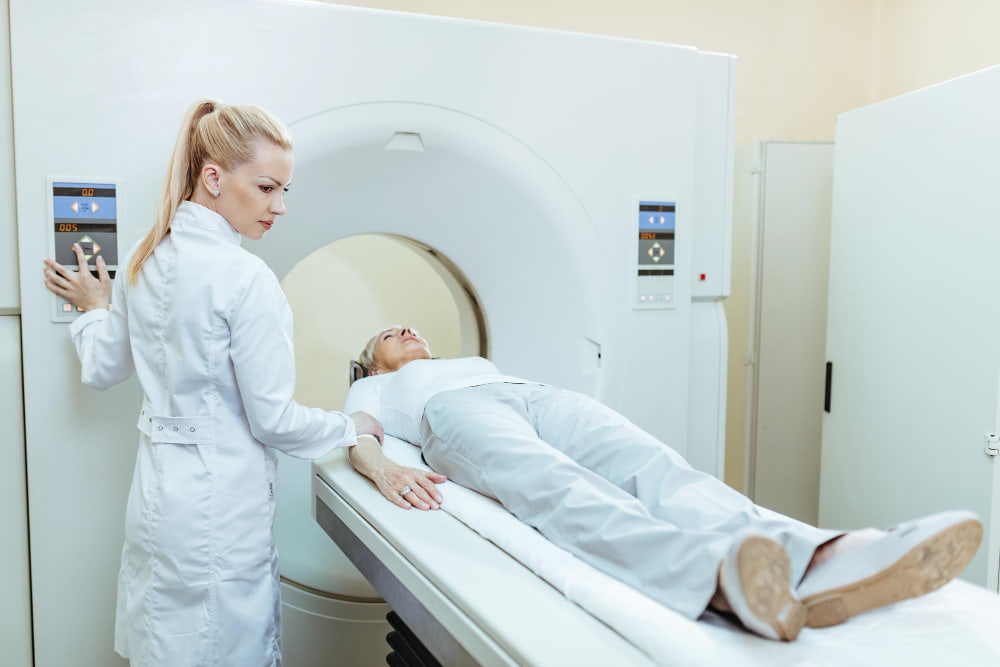

A calcium score test is a specialized CT scan that looks for calcium deposits in the coronary arteries, the blood vessels that supply oxygen-rich blood to the heart muscle. These deposits can be a sign of coronary artery disease, a condition in which fatty material and other substances build up inside artery walls. By measuring the amount of calcium in these arteries, doctors can better understand a person's risk of future cardiovascular problems.
The test is particularly useful for people who have no obvious symptoms but may have risk factors such as high cholesterol, high blood pressure, diabetes, smoking, or a family history of early heart disease. However, a calcium score alone cannot determine whether an artery is blocked or predict exactly when a heart attack might occur. Its value comes from combining the results with a person's medical history, other risk factors, and overall cardiovascular health.
Understanding the coronary calcium score, how the scan works, and what different results mean can help patients make informed decisions about heart health, preventive care, and treatment.
What Is a Calcium Score Test (Coronary Artery Calcium Test)?
A calcium score test, also called a coronary calcium scan or coronary artery calcium (CAC) test, is a noninvasive imaging procedure that uses computed tomography (CT) to detect and measure calcium deposits in the coronary arteries. It is designed to identify signs of calcified plaque, which can develop as part of atherosclerosis, a disease process in which plaque accumulates within artery walls.
The scan focuses specifically on calcium in the coronary arteries rather than measuring the calcium circulating in the blood. This distinction is important because blood calcium levels and coronary artery calcification provide different types of medical information.
The test produces a numerical result known as the coronary artery calcium score or CAC score. In general, a higher score indicates a greater amount of calcified plaque and is associated with a higher risk of cardiovascular events over time.
Doctors may recommend a calcium score test when they need additional information to estimate cardiovascular risk, particularly when the best approach to preventive treatment is not clear from conventional risk factors alone.
What Does a Coronary Calcium Scan Detect?
A coronary calcium scan detects calcium-containing deposits within plaque in the walls of the coronary arteries. These deposits can accumulate as atherosclerosis develops over many years.
The scan can help identify:
Calcified plaque: Calcium-containing material within coronary artery plaque, indicating that atherosclerotic changes have occurred.
Coronary artery calcification: The presence and extent of calcium deposits in the arteries supplying the heart.
Overall calcified plaque burden: A numerical estimate of how much calcified plaque is visible in the coronary arteries.
However, a CT calcium score does not show every type of plaque. Early or predominantly noncalcified plaque may not be detected, so a score of zero does not exclude all coronary artery disease.
The test also does not directly measure blood flow or establish the severity of an arterial narrowing. If symptoms or other findings suggest a more immediate problem, a doctor may recommend additional tests.
Who Should Consider a Calcium Score Test?
A calcium score test is generally most useful for adults who do not have symptoms of heart disease but whose estimated cardiovascular risk leaves uncertainty about preventive treatment. It can provide additional information when a doctor and patient are deciding whether cholesterol-lowering medication, such as a statin, may be appropriate.
A doctor may consider the test for people who:
Have borderline or intermediate estimated cardiovascular risk based on age, cholesterol levels, blood pressure, and other factors.
Have a family history of coronary artery disease, particularly heart disease occurring at a relatively young age.
Have high cholesterol or other risk factors that make their long-term cardiovascular risk difficult to estimate.
Want additional information to support a discussion about preventive treatment.
The test is not necessary for everyone. People already known to have coronary artery disease or those whose risk factors clearly indicate the need for treatment may not benefit from additional calcium scoring. It is also not the appropriate first test for someone experiencing possible heart attack symptoms, such as new chest pressure or sudden shortness of breath.
A calcium score test is a tool for selected patients, not a substitute for routine cardiovascular assessment or a universal screening test.
What Causes Calcium to Build Up in the Arteries?
Arterial calcification is the accumulation of calcium-containing minerals in the walls of blood vessels. In the coronary arteries, this process is commonly associated with atherosclerosis, a long-term condition in which plaque develops within artery walls.
Plaque forms when cholesterol, fats, inflammatory cells, and other substances accumulate in the inner lining of an artery. Over time, the body may deposit calcium within this plaque. This process is known as coronary artery calcification, or atherosclerotic calcification.
The presence of calcium indicates that atherosclerotic changes have occurred, but it does not automatically mean that an artery is severely narrowed. The amount and distribution of calcified plaque, together with other clinical findings, help doctors assess cardiovascular risk.
Common Risk Factors for Coronary Artery Calcification
Several factors can increase the likelihood of developing calcified plaque in the coronary arteries.
Age: The likelihood of coronary artery calcification generally increases with age as plaque accumulates over time.
High LDL cholesterol: Low-density lipoprotein (LDL), often called bad cholesterol, contributes to plaque formation when excessive amounts circulate in the blood.
High blood pressure: Persistent pressure against artery walls can damage the blood vessels and contribute to cardiovascular disease.
Smoking: Tobacco exposure damages blood vessels and accelerates atherosclerosis.
Diabetes: High blood sugar over time can damage blood vessels and increase the risk of coronary artery disease.
Family history: Having close relatives who developed cardiovascular disease at an early age may indicate a greater inherited risk.
Physical inactivity and an unhealthy diet: These factors can contribute to high cholesterol, excess weight, high blood pressure, and diabetes.
Chronic kidney disease can also contribute to vascular calcification through disturbances in calcium, phosphate, and bone metabolism. This type of calcification may affect blood vessels beyond the coronary arteries and is not identical to the plaque-related process measured by a coronary calcium score.
Is Arterial Calcification the Same as Coronary Artery Disease?
Arterial calcification and coronary artery disease are closely related, but they are not interchangeable terms. Arterial calcification can occur in different blood vessels, whereas coronary artery disease specifically affects the arteries that supply blood to the heart muscle.
A CT calcium score measures calcified plaque in the coronary arteries. It does not provide a complete assessment of vascular calcification throughout the body, nor does it detect every form of plaque that may cause coronary artery disease.
A person may have noncalcified plaque even when no coronary calcium is visible. Conversely, someone with extensive calcification may have no current symptoms. This is why the calcium score must be interpreted alongside the person's symptoms, medical history, and other test results.
How Is a CT Calcium Score Test Performed?
A CT calcium score test is a quick, noninvasive procedure that does not require surgery, a catheter, or an injection of contrast dye. It uses X-rays to create detailed images of the heart and identify calcium deposits in the coronary arteries.
The procedure usually takes about 10–15 minutes, although the total appointment may be longer depending on preparation and reporting.
Before the Scan
The healthcare team explains the procedure and provides any necessary instructions. Depending on the facility's protocol, patients may be asked to avoid caffeine before the scan because it can affect heart rate. They should also tell the healthcare team if they are pregnant or may be pregnant.
The patient generally does not need sedation or an intravenous line. The scan is performed without contrast dye, which distinguishes it from some other types of cardiac CT examinations.
During the Scan
The patient lies on a scanning table that moves through the CT scanner. Small electrodes attached to the chest monitor the heartbeat so that images can be captured at the appropriate point in the cardiac cycle.
The patient may be asked to hold their breath briefly while the images are taken. The scanner records the heart and coronary arteries, and the images are then analyzed for calcium deposits.
The procedure is painless. Most patients can return to their usual daily activities immediately afterward.
After the Scan
A radiologist or another appropriately trained clinician reviews the images and calculates the calcium score. The results are then interpreted in the context of the patient's cardiovascular risk factors.
A high score does not automatically mean that an emergency procedure is needed. Instead, it may prompt a more detailed discussion about cholesterol management, blood pressure control, lifestyle changes, and whether additional cardiac investigations are appropriate.
Because the test uses ionizing radiation, the expected benefit should be weighed against the small radiation exposure. It is generally reserved for situations in which the result is likely to help guide medical decisions.
How Is the Coronary Calcium Score Calculated?
The most widely used method for cardiac scoring is the Agatston scoring system. This method identifies areas of calcium on CT images and considers both their size and density to calculate a numerical score.
The resulting Agatston calcium score reflects the total burden of detectable calcified plaque in the coronary arteries. Higher scores generally indicate more extensive coronary calcification and a higher risk of future cardiovascular events.
The score is usually reported in Agatston units (AU). It is not a percentage of arterial blockage, and it should not be interpreted as a direct measurement of how much blood can pass through an artery.
Doctors may also consider the patient's percentile compared with people of a similar age and sex. This comparison can help show whether the amount of calcification is relatively high for that person’s demographic group.
What Do Calcium Score Test Results Mean?
Calcium score test results are generally grouped into categories according to the amount of calcium detected. The ranges below are commonly used to interpret the Agatston score. Although they provide a helpful overview, the score must be considered alongside a person's age, symptoms, and other cardiovascular risk factors.
| Agatston Calcium Score | Level of Coronary Calcification | What It Generally Means |
|---|---|---|
| 0 | No detectable calcification | Lower short-term cardiovascular risk, although noncalcified plaque may still be present. |
| 1–99 | Mild | A small amount of calcified plaque is present, indicating coronary atherosclerosis. |
| 100–299 | Moderate | A greater burden of calcified plaque and increased cardiovascular risk. |
| 300–999 | Severe or extensive | Substantial coronary calcification associated with elevated cardiovascular risk. |
| 1,000 or higher | Very extensive | A particularly high burden of calcified plaque and significantly increased cardiovascular risk. |
These ranges are general interpretive categories, not a diagnosis of arterial blockage. A high score does not automatically mean that an artery is severely narrowed, and a low score does not rule out all coronary artery disease. A doctor should interpret the results in the context of the patient's medical history and overall risk.
What Is a Normal Calcium Score?
A calcium score of zero is generally considered the most reassuring result because no calcified plaque has been detected. However, there is no single score that can be considered normal for every person, regardless of age and other risk factors.
A score between 1 and 99 indicates that calcified plaque is present, even if the amount is small. A score of 100 or higher generally indicates a more substantial plaque burden, while a score of 300 or higher is associated with a greater risk of cardiovascular events.
The appropriate interpretation depends on the patient's age, cholesterol levels, blood pressure, smoking history, diabetes status, and family history. A doctor should explain what the result means for the individual rather than relying on the number alone.
What Is the Average Calcium Score by Age?
There is no single reliable average calcium score by age that applies to everyone. Coronary artery calcification becomes more common as people get older, but the amount varies considerably according to sex, inherited risk, lifestyle, and medical conditions.
An average calcium score by age chart can provide general context, but it should not be used to diagnose disease or determine treatment on its own. Doctors may instead compare a patient's score with age- and sex-specific percentiles to understand whether the amount of calcification is unusually high for their demographic group.
For example, a relatively low score in a younger adult may still be significant because calcification is less common at that age. In an older adult, a higher absolute score may be more common, but it can still indicate increased cardiovascular risk. Both the absolute score and the relative percentile can contribute to a more complete assessment.
What Does a High Calcium Score Mean for Life Expectancy?
The relationship between life expectancy with high calcium score results and overall cardiovascular health is complex. A high coronary calcium score is associated with an increased risk of heart attack, stroke, and other cardiovascular events over time. However, it cannot predict an individual's exact life expectancy.
The significance of a high score depends on several factors, including the extent of coronary calcification, age, blood pressure, cholesterol levels, diabetes, smoking, kidney function, and whether cardiovascular disease has already been diagnosed.
A high score is not a prediction that a heart attack will happen soon. It is a sign that preventive care deserves attention. Appropriate treatment can reduce cardiovascular risk even when calcified plaque is already present.
Can a Calcium Score of Zero Guarantee a Healthy Heart?
No. A score of zero is associated with a lower short-term risk of cardiovascular events, but it does not guarantee that the coronary arteries are completely free of disease.
Noncalcified plaque may be present before calcium deposits develop. In addition, people with diabetes, a strong family history of premature cardiovascular disease, current smoking, or certain inherited cholesterol disorders may remain at significant risk despite a zero score.
For this reason, a reassuring result should not lead patients to ignore high cholesterol, high blood pressure, or other established risk factors.
What Happens After a Calcium Score Test?
The next step depends on the result and the patient's overall cardiovascular risk. A calcium score test helps guide preventive decisions; it does not automatically determine which medication or procedure is necessary.
Treatment and Prevention After a High Score
If the scan reveals coronary artery calcification, the doctor may recommend measures to reduce the risk of further plaque development and cardiovascular complications.
Cholesterol management: Statins and other cholesterol-lowering medicines may be recommended to reduce LDL cholesterol and lower the risk of cardiovascular events.
Blood pressure control: Monitoring and treating high blood pressure can reduce strain on the heart and blood vessels.
Diabetes management: Keeping blood glucose within the recommended range helps protect the cardiovascular system.
Lifestyle changes: Regular physical activity, a balanced heart-healthy diet, smoking cessation, and maintaining a healthy weight can help reduce overall cardiovascular risk.
Further testing when indicated: Additional investigations may be considered if the patient has symptoms or if the clinical findings suggest that more information is needed.
A high calcium score alone does not mean that coronary angiography, a stent, or bypass surgery is necessary. Those decisions require separate clinical assessment and, where appropriate, tests that evaluate arterial narrowing or blood flow.
Can Arterial Calcification Be Reversed?
Established coronary artery calcification generally cannot simply be removed through diet, exercise, or medication. However, treatment can help slow the progression of atherosclerosis and reduce the likelihood of plaque-related complications.
Cholesterol-lowering medication can reduce LDL cholesterol and stabilize plaque, making it less likely to rupture and trigger a clot. Lifestyle changes also contribute to better cardiovascular health.
Importantly, a calcium score may remain stable or increase even when preventive treatment is effective. Changes in the score do not necessarily reflect treatment success or failure, so doctors generally assess progress through cholesterol levels, blood pressure, symptoms, and overall cardiovascular risk rather than relying on repeated calcium scans alone.
Calcium Score Test vs. Other Heart Tests
A calcium score test is one of several tools used to assess cardiovascular health. The most appropriate examination depends on whether the goal is to estimate future risk, investigate symptoms, or determine whether coronary arteries are narrowed.
Blood tests: Cholesterol and blood glucose tests identify important cardiovascular risk factors but do not directly show plaque in the coronary arteries.
Electrocardiogram (ECG/EKG): This test records the heart's electrical activity and can help identify certain rhythm abnormalities or signs of heart strain. It does not measure coronary calcium.
Echocardiogram: An ultrasound examination that assesses heart structure, pumping function, and valve function.
Cardiac CT angiography: A CT examination that uses contrast dye to visualize coronary arteries and assess plaque and narrowing. Unlike a standard calcium score scan, it can show noncalcified plaque.
Stress testing: Exercise or medication-based tests that assess how the heart responds to increased demand and may help investigate suspected ischemia, or insufficient blood supply to the heart muscle.
A cardiac CT scan is therefore not a single type of examination. The calcium score test and CT angiography answer different clinical questions, and neither should be selected without considering the patient's symptoms and risk profile.
How Much Does a Cardiac CT Scan Cost?
The cardiac CT scan price depends on the type of examination, the healthcare facility, the technology used, and whether the cost includes the radiologist's report and a cardiologist's consultation.
A coronary calcium scan is generally less complex than CT coronary angiography because it does not require contrast dye. However, prices can vary between hospitals and countries, and insurance coverage is not universal.
When comparing costs, patients should confirm whether the quoted price covers the scan, image interpretation, and any consultation needed to discuss the results. If additional tests are recommended, these may involve separate charges.
For international patients considering a calcium score test in Turkey, it is useful to clarify the scope of the examination and the arrangements for receiving a medical report that can be shared with their doctor at home.
Why Choose Medical Park for Cardiovascular Assessment in Turkey?
Understanding cardiovascular risk requires more than interpreting a single number. Medical Park Hospitals in Turkey provides cardiovascular assessment, diagnostic services, and treatment through its Cardiology and Radiology departments, helping patients understand their findings in the context of their medical history, symptoms, and other risk factors.
Depending on the clinical indication, the evaluation may include a cardiology consultation, laboratory testing, and appropriate cardiac imaging. The cardiologist can explain whether a calcium score test is suitable, interpret the results, and discuss preventive treatment or further investigations when needed.
For international patients, Medical Park's International Patient Services Center can help coordinate appointments, diagnostic procedures, and communication about medical reports. Patients can also discuss arrangements for receiving their results and sharing them with their treating physician at home.
A calcium score test can provide valuable information about coronary artery disease risk, particularly when preventive treatment decisions are uncertain. The most useful next step is to interpret the findings with a qualified clinician and develop an individualized plan to protect long-term heart health.




 Makaleye Dön
 E-Result
 WhatsApp